By: Dr. Sable Muntean
Missed part 6? Catch up here.
“Doing nothing” is a treatment option. We rarely present it that way, but patients choose it all the time, and when they do, they deserve to understand what they’re actually choosing.
This is a conversation most of us rush past or avoid entirely, usually because it feels uncomfortable to advocate for non-treatment. But there’s a version of this conversation that’s honest, respectful, and paradoxically one of the best things you can do for long-term case acceptance.
Name It as a Choice, Not a Default
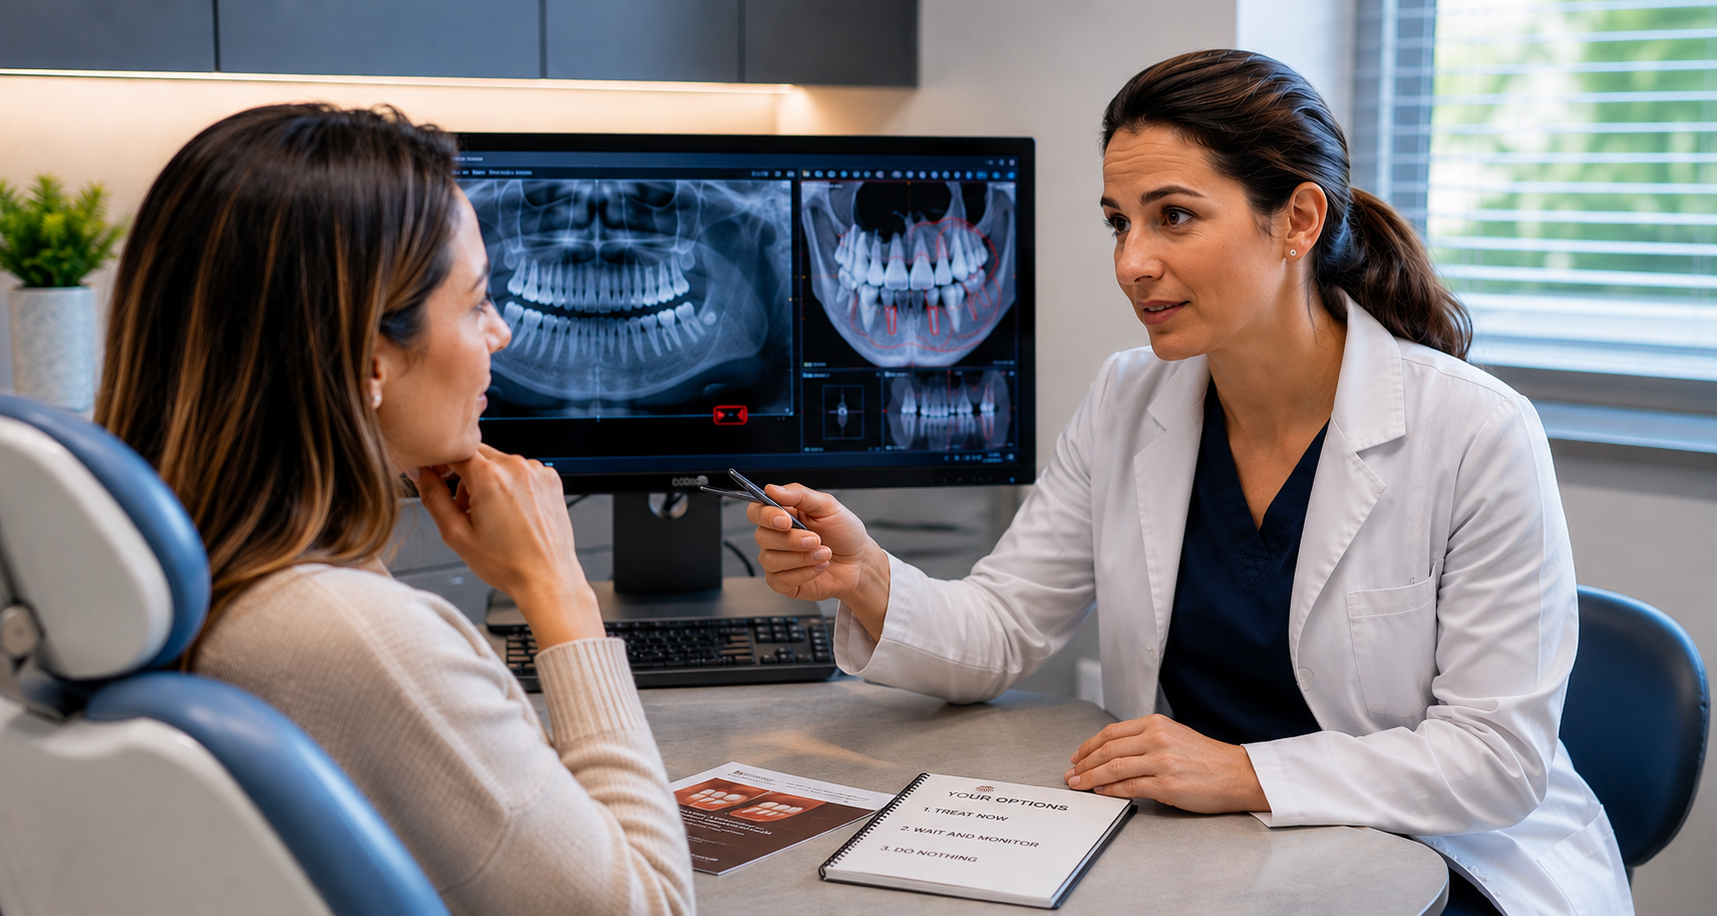
When patients leave without committing to treatment, they’re often not consciously choosing to do nothing, they’re just not choosing to do something yet. There’s a meaningful difference. If you explicitly frame observation or deferral as a choice, with known consequences, you shift the dynamic.
“One option is to wait and monitor. Here’s what we’d expect to see over the next six to twelve months, and here’s when we’d want to reassess”
…treats the patient like a partner. It also creates a framework for the follow-up conversation.
Be Specific About What “Doing Nothing” Actually Means
Vague warnings don’t change behavior. Specific, concrete information does.
“Over the next one to two years, we’d expect to see continued bone loss in this area, which may limit our implant options later, or require additional grafting that adds cost and time to the treatment”
…is something a patient can actually use to make a decision. “It’s going to get worse” is something they can rationalize away.
Avoid Catastrophizing, It Backfires
There’s a temptation to paint the worst-case scenario when a patient is hesitating, hoping urgency will tip them toward yes. This usually doesn’t work. Patients who feel manipulated by fear become defensive and dig in.
The goal is honest clinical information delivered without drama: here is what we observe, here is what tends to happen over time, here is what your options look like now versus later. Let the facts do the work.
Document the Conversation
This matters clinically and ethically. When you’ve discussed the risks of non-treatment and the patient has chosen to defer, document it. This protects you and creates a paper trail that becomes part of the ongoing conversation.
When the patient comes back six months later and something has changed, you can reference what was discussed, what was observed, and how the situation has evolved. That continuity builds trust and reinforces that your recommendations were never arbitrary.
Leave the Door Open Without Leaving Them Hanging
End the “doing nothing” conversation with a clear next step, even if that step is just a monitoring appointment.
“Let’s plan to reassess in six months. I’ll have my team reach out to schedule that, and in the meantime, call us if anything changes or you have more questions.”
This keeps the relationship active, signals ongoing care, and ensures that patients who are ready later know exactly how to re-engage.
Patients who feel respected during a deferred-treatment conversation come back. They also refer people. Honesty, delivered with care, is one of the most powerful long-term practice-builders you have.